
Pregnancy causes major hormonal and metabolic changes, and women with thyroid disorders may need additional monitoring during this time. Graves disease, an autoimmune condition that causes an overactive thyroid, can require particularly careful management during pregnancy.
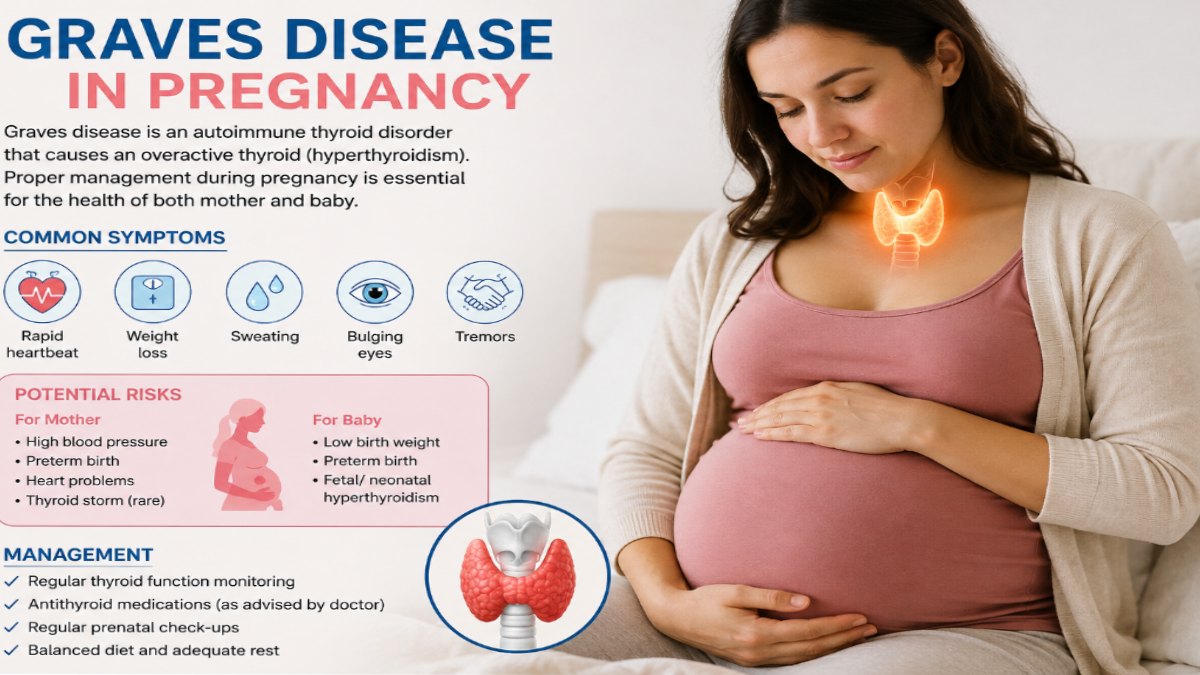
When hyperthyroidism is well controlled, many women with Graves disease can have healthy pregnancies. However, untreated or poorly controlled disease can increase the risk of complications for both the mother and baby. This is why early diagnosis, regular thyroid testing and coordinated prenatal care are so important.
What Is Graves Disease
Graves disease occurs when the immune system produces antibodies that stimulate the thyroid gland to make excessive amounts of thyroid hormones.
Related Articles


These hormones influence metabolism, heart rate and many other body functions. When thyroid hormone levels become too high, symptoms may include a fast or irregular heartbeat, anxiety, sweating, heat intolerance, tremors, difficulty sleeping, frequent bowel movements and unintentional weight loss.
Some people also develop an enlarged thyroid, known as a goitre, or changes affecting the eyes.
Pregnancy itself can cause symptoms such as fatigue, changes in appetite and a faster heartbeat, which can sometimes make hyperthyroidism harder to recognise. Appropriate blood tests are therefore important when Graves disease is suspected.
Related Articles


Why Does Graves Disease Matter During Pregnancy
Pregnancy increases the body's demands and changes thyroid physiology. If Graves disease is uncontrolled, excess thyroid hormone can create health risks.
For the mother, poorly controlled hyperthyroidism may increase the risk of high blood pressure disorders of pregnancy, including pre-eclampsia, as well as heart complications and, in severe cases, thyroid storm.
For the baby, uncontrolled maternal hyperthyroidism may be associated with problems such as poor growth, preterm birth or low birth weight.
However, these risks are not inevitable. Proper treatment and monitoring can significantly improve pregnancy care.
Thyroid Antibodies Can Cross the Placenta
An important feature of Graves disease in pregnancy is the presence of thyroid-stimulating antibodies, often called TSH receptor antibodies or TRAb.
These antibodies can cross the placenta and, in some cases, stimulate the baby's thyroid even when the mother's thyroid function is controlled or she has previously received treatment such as radioactive iodine or thyroid surgery.
For this reason, healthcare professionals may check thyroid antibody levels during pregnancy and monitor the baby when indicated.
How Is Graves Disease Diagnosed
Diagnosis generally involves blood tests that assess thyroid function. These may include measurements of thyroid-stimulating hormone and thyroid hormones such as free T4.
Healthcare professionals may also test for thyroid antibodies when Graves disease is suspected or already known.
Because pregnancy naturally changes thyroid hormone levels and laboratory interpretation, test results should be assessed using pregnancy-appropriate reference ranges and in the context of the individual's health.
Treatment During Pregnancy
Treatment aims to control maternal thyroid hormone levels while minimising risks to the developing baby.
Antithyroid medicines are commonly used when medication is necessary. The choice and dosage may change during pregnancy because certain medicines have different safety considerations at different stages.
Doctors generally aim to use the lowest effective dose needed to control maternal hyperthyroidism.
Patients should never start, stop or change thyroid medication without medical guidance. Treatment decisions need to be individualised by an obstetrician, endocrinologist or other qualified healthcare professional.
What About Radioactive Iodine Treatment
Radioactive iodine is a standard treatment option for Graves disease outside pregnancy, but it must not be used during pregnancy because it can cross the placenta and damage the developing baby's thyroid.
Women who have received radioactive iodine treatment in the past should inform their healthcare team, especially if they are pregnant or planning a pregnancy.
Monitoring the Baby
When a mother has Graves disease, clinicians may monitor the pregnancy more closely depending on thyroid antibody levels, thyroid hormone control and other risk factors.
Ultrasound examinations can sometimes be used to assess fetal growth, heart rate, amniotic fluid and signs that could suggest fetal thyroid dysfunction.
Not every woman with Graves disease will require the same degree of fetal monitoring. The care plan depends on individual circumstances.
Planning Pregnancy With Graves Disease
Ideally, women with known Graves disease should discuss pregnancy planning with their healthcare team before conception.
Getting thyroid function under good control before pregnancy can reduce complications and allow the treatment plan to be reviewed in advance.
Women should also tell their doctor about all medications and supplements they take. Thyroid treatment may need to be adjusted as soon as pregnancy is confirmed.
Symptoms That Need Prompt Medical Attention
A very rapid or irregular heartbeat, severe shortness of breath, chest pain, extreme agitation, confusion, high fever or a sudden severe deterioration in health can indicate a medical emergency.
Pregnant women with Graves disease who develop concerning symptoms should seek urgent medical attention rather than assuming the symptoms are simply part of pregnancy.
After Delivery: Monitoring Still Matters
Graves disease does not necessarily disappear after pregnancy. In fact, autoimmune thyroid activity can change during the postpartum period, and some women experience worsening symptoms after delivery.
New mothers should continue follow-up with their healthcare provider and discuss symptoms such as racing heartbeat, unexplained weight changes, tremors, anxiety or marked fatigue.
Breastfeeding decisions should also be discussed with the treating clinician because medication choice and dosage may need to be considered in relation to lactation.
Graves disease in pregnancy requires careful management, but a diagnosis does not mean a healthy pregnancy is impossible. The key is maintaining appropriate thyroid hormone control and attending regular prenatal and thyroid follow-up appointments.
Because untreated hyperthyroidism and excessive thyroid medication can both create problems, treatment needs to be carefully balanced by qualified healthcare professionals. Women with Graves disease who are pregnant or planning pregnancy should work closely with their obstetric and thyroid-care teams to create an individualised plan for protecting their health and supporting their baby's development.
Medical note: This article is for general education and does not replace personalised medical advice. Pregnant women with Graves disease should follow guidance from their obstetrician and endocrinologist regarding testing, medication and monitoring.


Comments 0